Last year we marked the fourth centennial of the arrival of the first Africans brought to Virginia in the transatlantic slave trade.
The history of humans enslaving other humans goes back thousands of years. The basis for this has varied: some have been enslaved after being captured in wars; others in a form of permanent indentured servitude because of debt; and still others in extreme versions of class or caste systems in which some people spent their lives in a condition of servitude to others because the relation of one group (we might call them peasants or serfs) to another (nobility or aristocracy) was one of being treated as property: that some humans owned other humans was a feature of a society or culture.
Enslaved Africans brought to the New World were not, however, simply humans owned by other humans. They were regarded as less than human, more a distinct species than a race. They were mostly employed as beasts of burden and were bought and sold like livestock.
In the British colonies of North America there developed exceptions to this treatment of enslaved Africans as less than human. A slave might serve as a household servant, a nanny, or a wet nurse. On a plantation a slave might be a foreman or overseer of other slaves, responsible for managing their labor and maximizing their output, a sort of surrogate master who might employ such tools of enforcement as the whip. Having such a relatively elevated status could mean a lower likelihood of being sold as chattel. A slaveholder might come to regard such a slave almost as a member of the family and decide to render the servitude impermanent by providing for the slave to be freed after many years, sometimes upon the death of the owner.
But these were exceptions to the rule of having a sub-human status. In general slaves continued to be bought and sold as beasts of burden. When they reproduced, offspring were viewed as the products of breeding farm animals. Little or no thought was given to the notion that an adult male, an adult female, and the children produced by their sexual intercourse constituted a family, and such thinking did not enter into decisions about selling them when doing so would permanently separate them.
************************
In the 1970s I attended an academically selective public high school that drew students from all over the city. There were black classmates I held in high esteem because they were intellectually gifted, or talented musicians, or accomplished athletes who led my school's teams to championships. A few I had the good fortune to get to know well, forming deep friendships.
When I was in college and spent a summer driving a taxi - my first blue collar job - I was exposed to - in fact immersed in - the society of white working class fellow employees.
In general the city in which I was born and raised was extremely segregated. Nearly all of Philadelphia's neighborhoods were overwhelmingly white or black, typically virtually 100% one way or the other. My cab-driving coworkers came primarily from a working class neighborhood that was 100% white.
While I was by no means unfamiliar with racism, the content of some conversations astonished me, because it was not until that summer that I understood how some Whites regarded Blacks as less than human, a distinct species, referring to them as "animals" or even "things," statements about them often dripping with contempt.
At the age of 18 I had no idea how to respond to this - and so I didn't, except internally, where my response was to be shocked, appalled, horrified. Perhaps I sensed that nothing I might say could influence such thinking. And I was certainly too timid to try. Although I didn't know it at the time, I was an enabler.
The city's political milieu was hardly encouraging. The mayor was Frank Rizzo, police commissioner turned law-and-order politician, an unabashed racist whose treatment of the residents of black neighborhoods was disgraceful. Few black officers were added to the force when he was commissioner, and his tenure as mayor was marked by incidents of racist brutality and oppression.
The Black Lives Matter movement was formed nearly seven years ago. Only gradually did I come to realize that the movement was truly needed. My initial reaction was, "Of course black lives matter." It was not clear to me what, exactly, was the point of this statement.
Gradually I realized that there was good reason for making the statement, through the name of the movement and its myriad actions. News reports of incidents told the same story again and again: city police departments, both leaders and rank-and-file officers, conducted themselves as though black lives do not matter. City government officials' responses to such incidents ranged from indifferent to ineffectual.
When Black Americans are subjected to police brutality, the consequences span a gamut of effects, from injury, both emotional and physical, to death. It is all unmistakably dehumanizing. Yet rather than taking away the humanity of its victims, it flatly denies their humanity's very existence.
Black lives matter. They do not matter more than the lives of other members of our society. Black lives do not matter more than "blue lives." Black lives do not matter to the exclusion of the importance of others' lives. This insistence that black lives matter matter is necessary because they are in constant danger in the USA in a way that others are not, the result of a long history of seeing Blacks as less than human. Indeed, "structural racism" and "institutional racism" are mere euphemisms for the attitude that Blacks are less than human.
The statement made by the name of the movement conveys one simple and important truth: Black Lives Matter, and all of what we countenance in American society that denies that statement's verity must stop.
Friday, June 5, 2020
Friday, May 8, 2020
Responsible Citizenship in a Pandemic
As restrictions on various activities are eased this month, it will be very important for all of us to adhere to measures recommended to mitigate contagion: wearing masks, social distancing, and meticulous attention to personal hygienic practices such as hand washing.
It is being emphasized that these are necessary to prevent a steep rise in COVID-19 cases - and, ultimately, deaths.
It may be instructive to look a bit further at the practical consequences of doing - versus not doing - what is recommended. Let us call the recommendations - masks, social distancing, hygienic measures - the "triad."
Scrupulously implementing the triad - or failure to do so - has predictable results.
Of those who get infected with the virus, some will have minimal or no symptoms - referred to as "subclinical" infection. Many others, however, will feel ill enough to experience definite effects on their ability to engage in all their usual activities. Some will get sick enough to be hospitalized, and some of those will require intensive care.
Some who get infected will transmit the infection to others, for a "multiplier" effect.
Here are some things that will happen as a direct consequence of not adhering to the triad:
1. You will be more likely to get sick enough to miss work. This affects workplace productivity. It may place an additional burden on co-workers who must pick up the slack. It is harmful to the employer's bottom line - which is likely, ultimately, to be bad for you and your co-workers.
2. You will be more likely to get sick enough to require hospitalization, thereby consuming healthcare resources that could otherwise have been devoted to caring for others and driving up society's overall healthcare costs.
3. You will be more likely to become critically ill, thus requiring intensive care - the most costly utilization of healthcare resources.
4. You will be more likely to transmit the infection to others, thereby multiplying the effects enumerated as 1, 2, and 3 above.
5. Among those you may infect will be healthcare workers, despite their best efforts to keep from catching it from their patients. This may cause them to miss work, placing additional burdens related to cost and productivity on the healthcare system. (Sickness among employees is costly for hospitals, which must pay premium wages to those working overtime to cover.) It also increases the risk that healthcare workers will then transmit the infection to others, including their co-workers and their families - and other patients who are in the hospital for unrelated reasons.
Thursday, May 7, 2020
Socialism and the Pandemic
The right wing of US politics takes every opportunity to condemn socialism, often citing Venezuela and Cuba as countries where socialism has been associated with economic dysfunction and poor decision making, not merely ignoring the role of authoritarianism but claiming that socialism requires an authoritarian regime to govern.
Conspicuous by its absence is mention of Denmark - you know, that country where McDonald's workers earn a living wage rather than being regarded as kids in their first jobs doing it for pocket money while in reality still financial dependents of their parents. No, Denmark is not considered a socialist nation, as it has many features of a market economy side-by-side with high taxes and an extensive array of social welfare programs. And it certainly does not satisfy the classic definition of socialism in which the means of production are controlled by the State. But there is a great deal about the way Danish society works that Americans - especially those on the right - regard as socialist.
What did Denmark's government do about shutting down its economy for the pandemic? It told everyone there would be a freeze. Companies not in essential businesses would simply stop doing business. They would not terminate or furlough any employees, but instead keep them on the payroll. Those businesses would receive government assistance sufficient to cover their residual expenses, while employees would receive their paychecks from the government, essentially keeping pace with what they were earning.
Denmark has a strong economy. Not strong like President Trump says the US economy is, but strong in reality. The national treasury was brimming with budget surpluses, so there was enough money to cover the financing of the freeze for several months without incurring debt.
And now the Danish economy is reopening, as broadly and widely as any in the West - more so than most - with population-adjusted numbers of COVID-19 cases and COVID-19 deaths comparing favorably with the rest of Europe - and with the US. Population-adjusted cases for Denmark are 45% of the US number; deaths, 39%.
When the Danish government first announced how it was going to manage the economic shutdown, it was estimated that for the USA to do the same thing, it would cost between $2T and $2.5T. Perhaps you've noticed that we have already appropriated more money than that, yet the unemployment rate has soared, and other economic indicators are calamitous, with widespread effects on Americans that have people desperate to put an end to restrictions despite statistics that portend disastrous increases in cases and deaths.
Maybe there is no way we could have done what Denmark did. It would have been so alien to the way our economy operates that a proposal to do such a thing would have been regarded as preposterous in the halls of Congress.
But let us be honest: the approach taken by Denmark is undeniably socialist, and the strength of the Danish economy that made it so easy to decide to do it exists despite the many aspects of that nation's economy that are socialist in character.
Let's broaden our view of socialism beyond Castro's Cuba and Venezuela under Chavez - the "socialism" America's right wing loves to hate - and acknowledge that it can work very well, indeed.
Tuesday, May 5, 2020
Truth in Science
For my entire adult life I have been a student of the philosophy of science with a keen interest in the subject of truth in science.
In the midst of this pandemic, it has struck me how many people - with no training in scientific disciplines - set forth assertions of what they believe to be facts.
In the Second Century the Greek mathematician and astronomer Ptolemy developed a mathematical model of an Earth-centric universe. Such a model, to gain acceptance as scientific theory, must be consistent with all known observations. To retain its status, it must then predict future observations: as they are made, the model must be consistent with them, too.
Ptolemy's model was complex, but it fit so well that a heliocentric model of our solar system posited a few centuries earlier by Aristarchus was superseded.
The Earth-centric model was very comfortable for humanity, which had long thought of our position in the universe as being at the center, as we believed its Creator had made us in His image.
It was not until the Sixteenth Century that mathematician and astronomer Copernicus developed a compelling heliocentric model. In the following century Kepler set forth a model of elliptical orbits, and Galileo made detailed observations with increasingly powerful telescopes that were consistent with the model of Copernicus, and not of Ptolemy - essentially proving Ptolemy wrong after fifteen centuries.
We have known that certain diseases are caused by infectious agents only since the 19th Century, thanks to the work of men like Pasteur and Koch.
Virology is relatively young. While Jenner (smallpox) and Pasteur (rabies) developed vaccines against diseases now known to be caused by viruses, the infectious agents responsible were poorly understood. The first virus to be studied by electron microscopy - essential because viruses are too small to be viewed with a light microscope - was the tobacco mosaic virus, in the 1930s.
The great influenza pandemic of 1918, then, occurred when virology was in its infancy. We have learned a great deal about viruses in the last century: indeed, we have arrived at a point at which we are able to isolate viruses, study their structure with electron microscopy, and characterize the proteins and genetic material (DNA or RNA) of which they are made. We can even sequence the genome of a virus.
Yet there are still secrets to be elucidated about what makes some viruses use humans as hosts, what factors enable viruses to cross from one host species to another, why some viruses are more lethal than other related strains, and why some are more readily transmitted from one human to another.
Then there is the fascinating subject of how viruses change over time, with genetic mutations and minor modifications of their protein structures.
Now that you have some sense of just how much we know about viruses - and, more important, how much remains to be learned - perhaps you can understand why sometimes expert opinions on specific points may diverge. When you layer over this the complexities of human behavior that influence the interactions between viruses and the host species, you get some sense of the extremely challenging field of the epidemiology of viral diseases.
All of this is what scientists are up against when they try to figure out the best ways of facing a pandemic.
Now imagine that you are an elected official or a government regulator trying to make decisions about protecting the public, completely dependent on advice from experts who are, in turn, frantically gathering and interpreting a constant stream of new data.
In a situation like this it is critically important to recognize what we don't know. Yes, we still have to make decisions. But when the people trying to make the decisions - relying on the best advice available from those who know the most in a discipline full of unknowns - make decisions you don't like, just say you don't like those decisions. Don't imagine you have the knowledge to support a coherent argument that the decisions are wrong - if those decisions are made after careful consideration of the best advice to be had.
And if you believe you know the truth of the science, please remember Ptolemy.
Thursday, April 30, 2020
Remdesivir: First Glimpse of the ACTT
The National Institute of Allergy and Infectious Disease (NIAID) has issued a press release about the results of the Adaptive COVID-19 Treatment Trial (ACTT).
As described on the website <www.clinicaltrials.gov>, this is a randomized, placebo-controlled trial of the anti-viral drug remdesivir, administered intravenously for ten days.
No data from the study have been released for public scrutiny thus far. It is unclear whether this will be done before a formal manuscript is prepared and submitted for publication in a peer-reviewed medical journal.
The primary endpoint was time to recovery. This was defined as no longer requiring in-hospital care (including oxygen therapy) - or, for non-hospitalized patients, no longer requiring home oxygen and having no limitations on activities. [As the drug was administered in hospital, the latter description presumably was intended to include patients discharged while still requiring oxygen at home.]
The study failed to show a statistically significant difference in mortality. The NIAID press release says the results "suggest" a mortality benefit. In the language of medicine it is said there was a "trend" toward a certain outcome. That means if the study had enrolled a larger number of subjects, the difference might have achieved statistical significance, but we don't know that.
The statistically significant difference that did emerge was in the primary endpoint, time to recovery. For the placebo group, the median time was 15 days, while it was 11 days for the remdesivir group. (Median means half the subjects took less time, half took longer. One might imagine that using "mean," the arithmetic average, could tell a different story, depending on the time distribution of recovery, but only the raw data could tell us that.)
How can we put these results in context as we await more details?
Consider that patients with seasonal influenza are commonly prescribed oseltamivir (Tamiflu), for which the time-to-recovery data are less impressive: when initiated within 24-48 hours of onset of symptoms, oseltamivir makes a difference of about one day.
So remdesivir looks better than that, and if it shortens hospitalizations, and isn't terribly expensive (which we don't know yet), it will also prove cost-effective.
NIAID Director Dr. Anthony Fauci is being quoted as saying remdesivir is now the "standard of care." This is both premature and imprecise. The term "standard of care" refers to what a reasonable and prudent physician would do, and it is hard to say that the US population of reasonable and prudent physicians would order this drug when they haven't even been able to get a good look at the results of the clinical trial. More appropriate would be to say that the drug should become standard treatment, because it actually appears to do something useful, and that is superior to not giving a drug with potential benefit.
It is anticipated that the FDA will promptly issue an emergency use authorization, which is a preliminary step that may be followed by formal approval after an FDA panel has been able to review the raw data from the trial.
As you might imagine, it is unclear how soon Gilead, the manufacturer, will have the capacity to produce hundreds of thousands (or even millions) of doses to treat all the patients hospitalized with COVID-19 now and in the coming months.
Gilead CEO John O'Day was quoted yesterday as saying the company has enough remdesivir for "more than 50,000 treatment courses" and will have 140,000 by July - and could then ramp up from there.
O'Day also said that "from July on, we’re going to work very closely with the government and with health care systems to make sure that it’s accessible, that it’s affordable to governments. We’re going to make sure that access is not an issue with this medicine."
Monday, March 9, 2020
Universal Health Care - a Personal Perspective
The latest figure I've seen for the USA is that about 11% of Americans don't have health insurance. Tens of millions more have coverage with premiums, co-pays, and deductibles that either wreak havoc on the family budget or make them effectively uninsured, because they never seek medical care unless they are quite certain they have something very serious.
I'm not one of those. (I do tend to seek medical attention only if I think I have something very serious, but that's unrelated to health insurance; it's just the way I am.) I'm one of the very fortunate ones. I have excellent health insurance through my wife's employment, and her job (knock on wood) seems to be very stable.
A few years ago I developed an unusual heart condition, the evaluation and treatment of which has been costly.
Today I needed to gather up statements of what I paid in calendar 2019, to submit for reimbursement from a health savings account (HSA) - that device that enables us to pay for our out-of-pocket expenses with untaxed dollars, at least to the extent that we are able to forecast them. (It's like the old TV show "The Price is Right," in that you want to get as close as possible without going over your expenses, because if you don't use it, you lose it.)
After some time-consuming and irksome phone calls, I was able to get the information I needed online, as I hadn't saved all those tree-killing paper statements.
I believe we have a family deductible of "only" $1,000 a year, so I knew I would cover the amount that we put in the HSA, which was less than that.
I looked at the charges billed for all of the medical evaluation and treatment I received in calendar 2019.
I did not have major surgery. (Most of us know how expensive that is just from the information we get from stories in the news.)
Yet my total charges for the year were just shy of $450,000.
Without health insurance, I would be bankrupt or dead (or both, in that order, I suppose).
My cardiac condition is not the kind you get because of advanced age or unfortunate lifestyle choices (smoking, dietary over-indulgence, being sedentary). We so often think of America's health problems as being self-inflicted, and many of them are, to some degree. Not this one. Nope, nobody's fault. Just bad luck.
If this bad luck had been coupled with the kind of bad luck that afflicts thirty-some million Americans - being uninsured - my life would be a financial calamity, to put it very mildly.
What is the moral of this story?
Every American who lacks health insurance is just one unlucky roll of the dice from financial disaster. It is completely unacceptable that people facing dire threats to their health must simultaneously spend time with lawyers navigating bankruptcy proceedings.
I happen to like doctors better than lawyers, but that's just me. Nevertheless, I think people who are seriously ill or injured should focus on their health - not on the fact that everything they've worked for their whole lives is now gone.
Sunday, March 8, 2020
COVID-19: What's the Big Deal?
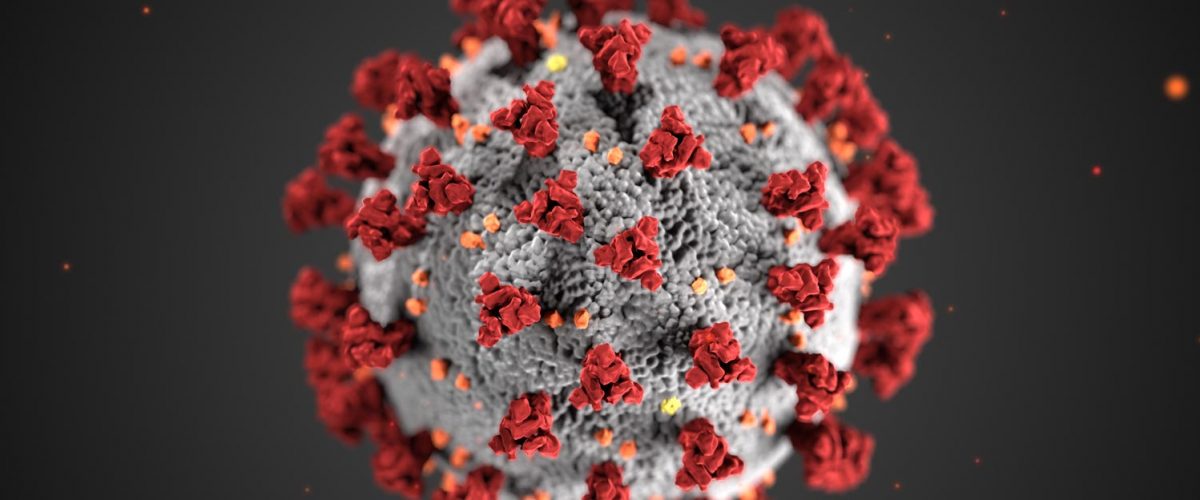
![]() |
| The proteins on the surface look like a crown, as in coronation |
As is true for influenza, illness caused by COVID-19 can range from very mild to severe. So why are we more worried about it than we are about seasonal flu?
The answer lies in part of the original name - before COVID-19 was adopted. It was called "novel" coronavirus. Novel doesn't mean the virus likes to read fiction, any more than the "corona" part of the name means it's connected to Corona beer.
Novel means new. Not new in the big scheme of things. New to humans, after making the leap from an animal species.
How can that cause so much trouble?
It means that it is new to our immune systems.
Let's say we take a group of 100 people who are well, put them in a room, and then add a person with seasonal influenza. That person can spread the flu virus to the others in the room. But not so easily. Each time a person who comes into contact - of the sort that lends itself to transmission - with the infected "index case," either of two things can happen. The new contact gets infected, and experiences illness.
Alternatively, if the new contact has some immunity, through vaccination against, or previous infection with, the same or closely related flu strains, the new contact will most likely not get sick, and will not be a source of contagion that - like the index case - threatens everyone else in the room.
The presence of immunity among people in the room means person-to-person spread will be limited. Thus, what epidemiologists call the "attack rate" will be reduced. (This is what epidemiologists sometimes call "herd immunity.")
Now, take the same group of 100 well people and add a person sick (even very mildly) with COVID-19. Nobody else in the room has any immunity, because this is a "novel" virus. So person-to-person transmission happens much more readily, and thus the "attack rate" will be much higher.
So we can see that even if COVID-19 is no worse than seasonal flu in the average person, the "novel" attribute enables it to spread quickly to a large number of people. And that really matters, because a certain percentage of people who get infected will die. That is called the "case fatality" rate. No matter what the case fatality rate is, the more people who get infected, the more will die.
Right now we aren't really sure how the case fatality rate compares with seasonal influenza. We just don't have enough population data yet, and that makes it a moving target.
But there is reason to be concerned that it will be significantly higher than for seasonal flu. Again, this is because of the "novel" attribute.
It is believed that one of the reasons the Spanish Flu of a century ago, a novel strain, killed so many people - and especially so many young and previously healthy people - has to do with the immune response. If you have been exposed to other viruses that are similar, you will have a little bit of immunity. This helps in two ways. First, your immune system is at least a little "primed" to respond. Second, some of the immune system's response will be to produce partially-matching antibodies that can act as "blocking" antibodies that lessen the intensity of the overall immune response. And this is actually a good thing.
Why? Because a good bit of the effect of the virus on your body - especially on the respiratory tract - is the result not so much of the virus itself but the inflammatory aspects of the immune response. The "blocking antibody" effect can lessen the severity of the inflammation. You don't get that when you're infected by a novel virus. Since young, healthy people typically have the most intense immune response to any infectious agent, the lack of a "blocking antibody" effect means they can get very sick very quickly. Paradoxically, then, their risk of becoming seriously ill or dying may not be that much lower than it is for the elderly and infirm.
What does all this mean? If we start to see evidence of rapid "community spread" - and there is reason to think we will - the attack rate will be high, the number of cases will be high, and the number of deaths will be high.
So pay attention to all the advice you're getting from reliable sources on how to limit contagion.
For my entire career I have been telling patients and families who ask me how to avoid spreading an infectious disease from the "index case" in the family: "Lots of hand washing." This applies to everything from "pinkeye" to the common cold to influenza. And now to COVID-19.
Wash your hands!
Subscribe to:
Posts (Atom)