Thursday, April 30, 2020

Remdesivir: First Glimpse of the ACTT

The National Institute of Allergy and Infectious Disease (NIAID) has issued a press release about the results of the Adaptive COVID-19 Treatment Trial (ACTT).

As described on the website <www.clinicaltrials.gov>, this is a randomized, placebo-controlled trial of the anti-viral drug remdesivir, administered intravenously for ten days.

No data from the study have been released for public scrutiny thus far.  It is unclear whether this will be done before a formal manuscript is prepared and submitted for publication in a peer-reviewed medical journal.

The primary endpoint was time to recovery.  This was defined as no longer requiring in-hospital care (including oxygen therapy) - or, for non-hospitalized patients, no longer requiring home oxygen and having no limitations on activities.  [As the drug was administered in hospital, the latter description presumably was intended to include patients discharged while still requiring oxygen at home.]

The study failed to show a statistically significant difference in mortality.  The NIAID press release says the results "suggest" a mortality benefit.  In the language of medicine it is said there was a "trend" toward a certain outcome.  That means if the study had enrolled a larger number of subjects, the difference might have achieved statistical significance, but we don't know that.

The statistically significant difference that did emerge was in the primary endpoint, time to recovery.  For the placebo group, the median time was 15 days, while it was 11 days for the remdesivir group.  (Median means half the subjects took less time, half took longer.  One might imagine that using "mean," the arithmetic average, could tell a different story, depending on the time distribution of recovery, but only the raw data could tell us that.)

How can we put these results in context as we await more details?

Consider that patients with seasonal influenza are commonly prescribed oseltamivir (Tamiflu), for which the time-to-recovery data are less impressive: when initiated within 24-48 hours of onset of symptoms, oseltamivir makes a difference of about one day.

So remdesivir looks better than that, and if it shortens hospitalizations, and isn't terribly expensive (which we don't know yet), it will also prove cost-effective.

NIAID Director Dr. Anthony Fauci is being quoted as saying remdesivir is now the "standard of care."  This is both premature and imprecise.  The term "standard of care" refers to what a reasonable and prudent physician would do, and it is hard to say that the US population of reasonable and prudent physicians would order this drug when they haven't even been able to get a good look at the results of the clinical trial.  More appropriate would be to say that the drug should become standard treatment, because it actually appears to do something useful, and that is superior to not giving a drug with potential benefit.

It is anticipated that the FDA will promptly issue an emergency use authorization, which is a preliminary step that may be followed by formal approval after an FDA panel has been able to review the raw data from the trial.

As you might imagine, it is unclear how soon Gilead, the manufacturer, will have the capacity to produce hundreds of thousands (or even millions) of doses to treat all the patients hospitalized with COVID-19 now and in the coming months.

Gilead CEO John O'Day was quoted yesterday as saying the company has enough remdesivir for "more than 50,000 treatment courses" and will have 140,000 by July - and could then ramp up from there.

O'Day also said that "from July on, we’re going to work very closely with the government and with health care systems to make sure that it’s accessible, that it’s affordable to governments. We’re going to make sure that access is not an issue with this medicine."

Monday, March 9, 2020

Universal Health Care - a Personal Perspective

The latest figure I've seen for the USA is that about 11% of Americans don't have health insurance. Tens of millions more have coverage with premiums, co-pays, and deductibles that either wreak havoc on the family budget or make them effectively uninsured, because they never seek medical care unless they are quite certain they have something very serious. I'm not one of those. (I do tend to seek medical attention only if I think I have something very serious, but that's unrelated to health insurance; it's just the way I am.) I'm one of the very fortunate ones. I have excellent health insurance through my wife's employment, and her job (knock on wood) seems to be very stable.
A few years ago I developed an unusual heart condition, the evaluation and treatment of which has been costly.
Today I needed to gather up statements of what I paid in calendar 2019, to submit for reimbursement from a health savings account (HSA) - that device that enables us to pay for our out-of-pocket expenses with untaxed dollars, at least to the extent that we are able to forecast them. (It's like the old TV show "The Price is Right," in that you want to get as close as possible without going over your expenses, because if you don't use it, you lose it.)
After some time-consuming and irksome phone calls, I was able to get the information I needed online, as I hadn't saved all those tree-killing paper statements.
I believe we have a family deductible of "only" $1,000 a year, so I knew I would cover the amount that we put in the HSA, which was less than that.
I looked at the charges billed for all of the medical evaluation and treatment I received in calendar 2019.
I did not have major surgery. (Most of us know how expensive that is just from the information we get from stories in the news.)
Yet my total charges for the year were just shy of $450,000.
Without health insurance, I would be bankrupt or dead (or both, in that order, I suppose).
My cardiac condition is not the kind you get because of advanced age or unfortunate lifestyle choices (smoking, dietary over-indulgence, being sedentary). We so often think of America's health problems as being self-inflicted, and many of them are, to some degree. Not this one. Nope, nobody's fault. Just bad luck.
If this bad luck had been coupled with the kind of bad luck that afflicts thirty-some million Americans - being uninsured - my life would be a financial calamity, to put it very mildly.
What is the moral of this story?
Every American who lacks health insurance is just one unlucky roll of the dice from financial disaster. It is completely unacceptable that people facing dire threats to their health must simultaneously spend time with lawyers navigating bankruptcy proceedings.
I happen to like doctors better than lawyers, but that's just me. Nevertheless, I think people who are seriously ill or injured should focus on their health - not on the fact that everything they've worked for their whole lives is now gone.

Sunday, March 8, 2020

COVID-19: What's the Big Deal?

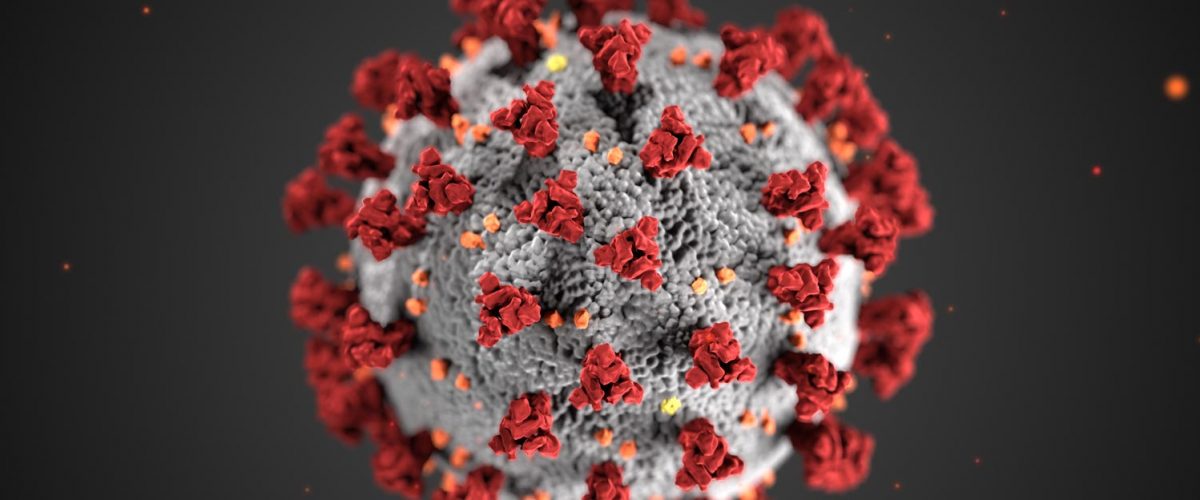
The proteins on the surface look like a crown, as in coronation
As is true for influenza, illness caused by COVID-19 can range from very mild to severe.  So why are we more worried about it than we are about seasonal flu?

The answer lies in part of the original name - before COVID-19 was adopted.  It was called "novel" coronavirus. Novel doesn't mean the virus likes to read fiction, any more than the "corona" part of the name means it's connected to Corona beer.
Novel means new. Not new in the big scheme of things. New to humans, after making the leap from an animal species.
How can that cause so much trouble?
It means that it is new to our immune systems.

Let's say we take a group of 100 people who are well, put them in a room, and then add a person with seasonal influenza. That person can spread the flu virus to the others in the room. But not so easily. Each time a person who comes into contact - of the sort that lends itself to transmission - with the infected "index case," either of two things can happen. The new contact gets infected, and experiences illness.

Alternatively, if the new contact has some immunity, through vaccination against, or previous infection with, the same or closely related flu strains, the new contact will most likely not get sick, and will not be a source of contagion that - like the index case - threatens everyone else in the room.

The presence of immunity among people in the room means person-to-person spread will be limited. Thus, what epidemiologists call the "attack rate" will be reduced. (This is what epidemiologists sometimes call "herd immunity.")

Now, take the same group of 100 well people and add a person sick (even very mildly) with COVID-19. Nobody else in the room has any immunity, because this is a "novel" virus. So person-to-person transmission happens much more readily, and thus the "attack rate" will be much higher.

So we can see that even if COVID-19 is no worse than seasonal flu in the average person, the "novel" attribute enables it to spread quickly to a large number of people. And that really matters, because a certain percentage of people who get infected will die. That is called the "case fatality" rate. No matter what the case fatality rate is, the more people who get infected, the more will die.

Right now we aren't really sure how the case fatality rate compares with seasonal influenza. We just don't have enough population data yet, and that makes it a moving target.

But there is reason to be concerned that it will be significantly higher than for seasonal flu. Again, this is because of the "novel" attribute.

It is believed that one of the reasons the Spanish Flu of a century ago, a novel strain, killed so many people - and especially so many young and previously healthy people - has to do with the immune response. If you have been exposed to other viruses that are similar, you will have a little bit of immunity. This helps in two ways. First, your immune system is at least a little "primed" to respond. Second, some of the immune system's response will be to produce partially-matching antibodies that can act as "blocking" antibodies that lessen the intensity of the overall immune response. And this is actually a good thing.

Why? Because a good bit of the effect of the virus on your body - especially on the respiratory tract - is the result not so much of the virus itself but the inflammatory aspects of the immune response. The "blocking antibody" effect can lessen the severity of the inflammation. You don't get that when you're infected by a novel virus. Since young, healthy people typically have the most intense immune response to any infectious agent, the lack of a "blocking antibody" effect means they can get very sick very quickly. Paradoxically, then, their risk of becoming seriously ill or dying may not be that much lower than it is for the elderly and infirm.

What does all this mean? If we start to see evidence of rapid "community spread" - and there is reason to think we will - the attack rate will be high, the number of cases will be high, and the number of deaths will be high.

So pay attention to all the advice you're getting from reliable sources on how to limit contagion.

For my entire career I have been telling patients and families who ask me how to avoid spreading an infectious disease from the "index case" in the family: "Lots of hand washing." This applies to everything from "pinkeye" to the common cold to influenza. And now to COVID-19.

Wash your hands!

Thursday, January 16, 2020

The Politics of Blame

Over the last couple of debates, as I've been watching Amy Klobuchar and have been mostly impressed with her performance - notwithstanding her calling Medicare for All a "pipe dream" - I have been aware that I have had reservations about her since last summer because of something she said in a debate. And it didn't have anything to do with her policy positions being "pragmatic" instead of "progressive."

No, it was something she said to which I recall having had an immediate, personal, visceral reaction. And today, having watched the last debate before the Iowa caucuses, earlier this week, I tried to remember what it was.

So I searched my memory, and then Google. It was something she said that reflected on my profession and my specialty. It was about addiction to opioids. And it wasn't in response to a question on that topic. It was the lead in her closing statement - a part of the debate when viewers tend to listen very closely.


After thanking the city of Detroit for hosting the July 30 debate, she said:

"To win, we have to listen to people. And out there today is Casey Jo's mom. Casey Jo was a champion high school swimmer from a small town. She got sick, went to the emergency room, and got hooked on opioids. The last thing that she said to her mom was, "Mama, it's not my fault."  And she died."

To be fair, Senator Klobuchar did blame pharma, but that seemed to me an afterthought, probably because she led with "the emergency room." And we all know that what you lead with gets the most attention.

And the way she related it?

"She got sick, went to the emergency room, and got hooked on opioids."

I can tell you this: in emergency medicine we don't typically prescribe opioids for "sick," unless "sick" is terminal cancer with spread to places where it causes severe pain, or maybe kidney stones. And broken bones, which are not "sick."

I am fed up with people blaming emergency physicians for opioid addiction. There are studies that show even an initial, very limited Rx for opioids can put some people at risk for addiction. My colleagues and I know this, and we are judicious in prescribing. The percentage of all Rx pain killers prescribed by doctors in my specialty is tiny - and getting smaller all the time.

How sensitive are we to this issue? I'll tell you how sensitive.

In September of 2018 I fell and broke ribs. I knew I had broken ribs the moment I picked myself up off the floor, because I know anatomy and patterns of injury. And my diagnosis was confirmed by the fact that the area was very painful with breathing or movement of my torso and stayed that way for 6 weeks.

Guess what I didn't do? I didn't go to the hospital. I didn't need x-rays to make the diagnosis, and I knew no one would treat my severe pain with a prescription for a narcotic pain reliever. The cowboy in me would have to "walk it off." That's fine when you're walking, but I didn't get a decent night's sleep for over a month.

You read that paragraph right: I knew no one would prescribe a narcotic pain reliever for one of their own. That is how sensitive we are to the risk of addiction.

Yet Senator Klobuchar led her closing statement by talking about opioid addiction, and said it happens in the emergency room, to people who go there because they are "sick."

She's not my first (or second) choice, but I think Amy Klobuchar would make a fine president for this nation. I hope and trust that she would have smarter people advising her on matters of policy and how to frame them in her public speaking.

Tuesday, October 8, 2019

The Social Contract: A Concept Whose Time Has Gone - or Returned?

Two and a half centuries ago the French political philosopher Jean-Jacques Rousseau wrote a book called Du contrat social ou Principes du droit politique, translated (roughly) into English as The Social Contract.  Rousseau was one of several theorists who formulated ideas about the relationships among members of a society, and especially between society and the individual, during the European Enlightenment.  Along with Rousseau, Thomas Hobbes and John Locke were powerfully influential in the thinking of America's Founding Fathers and the Framers of the Constitution.


The idea of the social contract was advanced to provide the philosophical foundation for the governance of a nation: it is a framework upon which to build the relationship between the State and the individual, and a key to understanding the basis for members of a society choosing to act collectively through the State, deciding in what ways the interests of the individual should be made subordinate to those of society as a whole in order to benefit everyone.

Throughout American history the social contract has been the focus of tension between the State, which has been given agency to act for society's collective interests, and the individual.  This tension exists largely because of the traditional American emphasis on rugged individualism and personal responsibility.

The belief in rugged individualism often runs afoul of the limitations imposed by nature upon human beings.  There are many things people cannot accomplish without reliance upon their neighbors.  Sometimes this is because a single person is physically incapable of carrying out a task without assistance.  Commonly it is because it is necessary to bring to bear upon a project resources that are not, or even cannot be, possessed or controlled by one person or a small group.

On a small scale at the community level, this can be observed in the building of a house or the raising of a barn by the Amish in rural Pennsylvania or Ohio.


In a more "modern" context, the design and construction of a children's playground in suburbia may bring together adults from the community who contribute volunteer labor and seek donations of construction materials from local businesses.


Of course there are many things we need to do that require collective effort on a much larger scale.  The Interstate Highway System is a favorite example.  Many of us never learned, or learned and forgot, that in the early decades of our republic, there were strenuous disagreements about what government could or should undertake in the way of large-scale projects.  "Internal improvements" such as the construction of roads and canals were considered the domain of state governments, and there was only grudging acceptance of the notion that the national government should get involved in interstate projects.

For a long time I believed the question of how expansive should be the role of government, acting as agent for American society, was settled when the USA embraced the "American System" advanced by the early 19th-Century American Whig Party (the forerunner of the mid-Century Republican Party).  The American System relied for revenue on tariffs, which simultaneously protected American agriculture and manufacturing from European competition, establishment of a national bank to facilitate commerce, and a system of internal improvements (the above mentioned roads and canals) to enable transportation of goods and speed the development of a national mercantile network.

This past weekend I came across stunning evidence that what I had begun to suspect was the abandonment of the social contract was really happening.  An essay was published in the NY Times about a community in rural Arkansas in which there was a backlash against spending money on a new library and a librarian well qualified to run it.  I'm hoping you'll read it, so I am not going to spoil it for you.  I'll just say that it reminded me of how my community library was a place of refuge in my youth, and the writer's account gave me a sense of deep sorrow about where American society is going.

This photo is from a piece about the best places to live in Arkansas.
A community that doesn't want to pay for a library would not make my list.
The essence of the story is that people don't want to pay taxes for anything that will not benefit them directly.  Many years ago I was challenged to overcome that resistance by the need for a new recreational facility in a development whose homeowners' association I served as president for 13 years.  The frustrations of getting people to understand the concept of community were endless.

On a truly national scale I see the same tensions now.  They rise up between those who believe access to basic healthcare is a universal human right, and those who reject that idea.  I see it in the conflict between Americans who recognize that we have long used public dollars to finance a level of education that prepares young people to compete for good jobs, and realize a high school education falls short, and those who had no help paying for college for themselves or their children and are damned if they are going to help anyone else.

I also see it in the strenuous disagreements between people who believe we should act through the agency of the state to ameliorate poverty, and those who believe only private charity should have that responsibility - because unlike government, private charity can sort out the deserving from the undeserving poor - even though private charity has never had the resources to address poverty on a national scale.  Accompanying that fundamental disagreement is the matter of turning a blind eye to the central inadequacy of a private-charity approach to solving social problems: it allows the well-to-do yet selfish among us to contribute nothing to the effort.

Two centuries after Rousseau and the other enlightenment political philosophers, John Rawls came along as the seminal American thinker and writer on issues in social justice.  Rawls seeks to answer the fundamental question of what kind of a society we should be building to try to make American life fair.  In his work A Theory of Justice (1971, revised in 1999), Rawls develops the concept of "justice as fairness," and he explores at great length how members of a society can go about developing consensus on the principles that should govern the way our social structures operate.

Nowadays the phrase "social justice" has been disparaged by those who cling to what I assert is the myth of rugged individualism and the belief that one can pull oneself up by one's own bootstraps.  (Giving just a moment's thought to this metaphor reveals the absurdity of it: bootstraps can be used to pull on a pair of boots, but certainly not to elevate one's position, either bodily or socioeconomically.)

I am cautiously optimistic that the presidential elections of 2016 and 2020 will serve to get more Americans thinking about just what our theory of justice should be.  When I look at the civil rights and great society efforts of the 1960s, and the fires burning at the center of today's Progressive movement, I find hope that we might emerge from the dark passage we have been in since the "me decade" of the 1980s - and once more discover that not only is there room in America for justice as fairness, but that is really what America must embody as its most important ideal. 

Tuesday, March 6, 2018

Judicial Fiat?

Madison's words are oft quoted by those opposing judicial activism,
 but he was actually referring to the courts expanding congressional authority
 beyond that specified in the Constitution.

A month ago I wrote about the Fair Districts movement in Pennsylvania and its lawsuit, led by the League of Women voters, seeking to have the absurdly gerrymandered boundaries of the Commonwealth's districts for the US House of Representatives declared unconstitutional.

That lawsuit succeeded: the Pennsylvania Supreme Court issued an order that the boundaries for the districts be re-drawn.

This has attracted national attention, as Pennsylvania is not the only state in which congressional districts have been a hot topic of political discussion.  North Carolina is just one other current example.

Last week (Monday, 2-26-18, to be precise), this subject was mentioned in the "Monday Political News Roundup" on the NPR broadcast of the KQED (San Francisco) Forum, a program hosted by Michael Krasny.  Krasny was talking with KQED's Senior Political Editor Scott Shafer, when Shafer referred to the decision as a "judicial fiat."

This was somewhat jarring to hear.  As you likely know, NPR is thought of as being part of the "liberal media" establishment, and San Francisco, home to KQED, certainly plays into that stereotyping.  Shafer is not known for liberal bias - and of course no political journalist should be - but a gay man from San Francisco is not someone I would expect to use a phrase that suggests a court is over-reaching its authority, given how the LGBTQ movement has relied so much upon the courts in seeking fair treatment.

The word fiat, taken in its most neutral sense, can mean simply an order to "make it so" (in the words of British naval officers, made famous by Captain Picard on Star Trek).  But the word is usually understood to suggest an arbitrary edict, in an authoritarian sense.

The purpose of this essay is not to take Shafer to task for his choice of words but to examine the question of whether the Pennsylvania Supreme Court was, in fact, over-reaching.

The Court found the gerrymandered districts unconstitutional.  So we should ask whether there is anything in the Pennsylvania Constitution or the US Constitution that provides a clear basis for that ruling.  The federal Constitution says simply that the drawing of district boundaries is the job of the state legislatures.  The Pennsylvania constitution, a much longer document (typical of state constitutions), contains specific language concerning the drawing of boundaries for state legislative districts but not congressional districts.

So what did the Commonwealth's high court do to find a basis for its ruling?

First, it declared that the language related to the drawing of state legislative districts - which specifies that districts should be compact and contiguous and should break up recognized entities such as counties and municipalities as little as possible (only where necessary to make district populations come out even) - to be entirely appropriate for extrapolation to congressional districts and to provide a "floor" - or minimum standard - by which these boundaries can be judged.

Second, it reviewed the political history of Pennsylvania, from colonial times through the drafting of the Commonwealth's first constitution and several revisions over many decades.  In an opinion exceeding 130 pages, the Court found that Pennsylvania has a history of trying to assure that its citizens have representation based on elections that are free and equal.  The consistent principle is that Pennsylvanians should not have less of a voice in their government because of where they live, or their nationality or ethnic background, or their political ideology.  Thus congressional district boundaries deliberately drawn to have exactly that effect are unconstitutional in the Court's view.

The state Supreme Court then reviewed the evidence presented by the parties to the lawsuit in support of or refuting the claim that existing boundaries were, in fact, deliberately drawn for the purpose of reducing the voice in government of Pennsylvania Democrats.  This evidence was somewhat limited by the refusal of Republican leaders in the state legislature to provide information about the methods they used in drawing the lines.

However, the strategy and tactics used by the Republicans have been no secret.  "REDMAP" is both what the GOP wants the US to look like (the Republican party's symbolic color red dominating the US map) and the acronymous name of its project for achieving that: the Redistricting Majority Project.  Just Google REDMAP, and settle in for hours of reading about how successful this has been in many US states, Pennsylvania prominent among them.  As I explained in last month's essay, Pennsylvanians distribute their votes for Members of Congress roughly equally between the two major parties, yet the state's congressional delegation of 18 in the US House of Representatives is not 9-9, but 13 Republicans and 5 Democrats (before the resignation of Tim Murphy last fall).  The situation is similar for the state legislature, which has strong Republican majorities in both houses.

So what are we to make of the Court's ruling?  It might seem even more like judicial fiat when you consider that the Supreme Court issued the new boundaries itself.  But its original order instructed the legislature to develop a new plan for congressional districts, send it to the governor for his approval, and then pass it along to the Court for its review.  The other branches of state government did not follow those instructions, knowing full well that Court-issued boundaries would be the result.  Legislative leaders of the two parties separately prepared new maps (on a partisan basis), and the Republicans sent theirs to the governor.  He did not approve, and prepared his own.  All of these were forwarded to the Court.  As no plan was submitted to the Court having been approved by the legislature and the governor, the Court, aided by its retained Special Master, drew up its own plan.

Just what is at issue here?  First, whether the state constitution, accompanied by state constitutional and legislative history, really affords a basis for the Court's ruling.  Second - given the US Constitution's provision assigning the task of drawing congressional district boundaries to state legislatures - whether the Court was sufficiently deferential to legislative authority.

Any time someone does not like a court ruling that is at odds with what legislators have done, the court can expect to be accused of "legislating from the bench" or of "judicial activism."

In the case of this Pennsylvania Supreme Court ruling, legislators have proposed impeaching the justices who voted in the majority, and the ruling has been appealed to a panel of federal court judges as well as to the US Supreme Court in a separate action.

Few things are of such keen interest to students of political science as a battle between branches of government over separation of powers.

If you are a "strict constructionist," you are likely to object to the Court's ruling, as it does not rely on the plain language of the state constitution (which does not specify criteria for congressional districts) and seems to flout the US Constitution (which assigns authority to state legislatures).  If you believe in the importance of examining constitutional and legislative history, which the Court does at great length in its opinion, you will reach the opposite conclusion.  Yesterday's Pittsburgh Post-Gazette offered a glimpse of this difference of opinion within the Thornburgh family.

Here is an update of the situation, published yesterday in The Morning Call, an eastern Pennsylvania newspaper.  At this point the pundits' consensus view seems to be that the federal court challenges will fail, and the new districts will be in effect for the primary to be held May 15th.  Right now congressional candidates across the Commonwealth are circulating petitions, gathering signatures to get on the ballot for that primary.  As one of those candidates, I would like the federal courts to stay out of this, as we have had so many screwball twists and turns in this election cycle already, we really don't need another one.  But stay tuned!

Friday, February 16, 2018

Guns & Mental Health

A teenager returned to the high school in Parkland, Florida from which he had been expelled for behavioral problems.  Armed with a semiautomatic rifle, he shot about 30 students, killing 17.  Many who knew him at the school knew he was deeply disturbed, and that he had guns, and they had predicted that he would do exactly this.

News reports said the FBI was warned but did nothing.

When I read online commentary it seems to me that opinion is divided into two camps.  Guns are the problem.  Or mental illness is the problem.  Of course American gun violence is a complex matter, and the availability of guns and the prevalence of mental illness are both important factors.

Are we going to do something to reduce dramatically the availability of guns?  All the evidence points to No.  We have more firearms in the USA than we have people.  We had a ban on semiautomatic rifles for ten years, but it had little effect on supply, and it sunset without evident effect on crime, partly because these weapons are used in a tiny fraction of incidents in which people are killed with guns, even though they are used in a sizable proportion of mass shootings.  We may have another ban on these weapons, as the public demand to "do something" escalates.  Or we may not.

If we do, I predict it will have little or no effect on mass shootings.  First, weapons like the AR-15 used by the Parkland, Florida shooter will remain abundant unless there is an Australian-style confiscation, which seems exceedingly unlikely.  Second, anyone bent on a mass shooting does not need an AR-15.

Ask a "gun nut" who owns an AR-15 with 30-round magazines and a Glock pistol of heavy caliber (say, .40 or .45 or 10 mm) with 15-round magazines this simple question: given either weapon, with twice as many loaded magazines for the Glock as the AR-15 (to yield the same number of total rounds), is there any real difference in how fast you could shoot and kill how many people?

The answer will be No.  And if your response is, well, then, we have to ban semiautomatic pistols, too, I can assure you that is a much bigger hill to climb, as they have been in US civilian hands in vast numbers for well over a century.  The same is true for high-capacity (meaning more than ten rounds) magazines.  Given the large number of such guns and magazines in circulation now, and the "non-starter" status of any attempt at confiscation, this approach is just not an effective solution.

So, I have a simple idea that might make a small contribution.  Small contributions have the disadvantage of being small, but sometimes they have the advantage of being feasible, so consider this one in that light.

In the spirit of full disclosure, there are three things I should tell you about myself.  First, I am a doctor specializing in emergency medicine, with a longstanding interest in public health, and I've read a lot about the public health perspective on gun violence.  Second, I am a gun owner, and I have read a lot about the American gun culture.  I can tell you how gun owners think and feel, and I can explain the positions of the NRA and the other gun-rights advocacy groups that take an even harder line (believe it or not).  Third, I am running for Congress, so I think a lot about America's problems, including social problems, from the "there-oughta-be-a-law" viewpoint.  If a voter asks me what I am going to do, if elected, about gun violence, "I don't know" is not an acceptable answer.

I live in Pennsylvania.  In my state doctors have a legal obligation to report to the Department of Transportation drivers who have medical problems that may cause them to have episodes of loss of consciousness that would be dangerous if they happen while driving.  This affects mostly people with seizures, but diabetics with repeated episodes of low blood sugar, people with fainting spells of various causes, and alcoholics and other drug addicts who lose control of a vehicle because of an overdose are all reportable.

So how about this?  Why not ask a doctor who encounters a patient with behavioral problems such that, in the physician's judgment, this person should not have access to firearms, to make a similar report to an appropriate government agency?

How would that work?  Here are a few essential points.

1.  Doctors would need guidelines.  So form a panel of experts to create them.  What are the signs a doctor can recognize that mean a person is potentially dangerous in ways relevant to having access to guns?  Require all licensed physicians to learn these guidelines.  State medical boards already micromanage our continuing education, like requiring all licensed physicians to take two or three hours of online education about opioid prescribing and addiction, or child abuse, so this would be easy to do.

2.  Reporting in good faith would be legally protected.

3.  A person who is reported would be investigated with respect to whether s/he should have the right to possess firearms restricted.  There would be built-in due process involving appropriate parts of our legal system, with the right to appeal and the right to petition to have gun rights restored.

Would this identify everyone who is emotionally unstable and shouldn't have guns?  Of course not.  But what do we do now?  The people who are disqualified are those hospitalized involuntarily because of mental illness, and those who are adjudicated mentally incompetent.  That is a small portion of the population of people who shouldn't have guns because they are a potential danger to themselves or others.  And the expansion of the "pool" adopted during the Obama Administration, and reversed by Trump, that would have added people judged by the Social Security Administration as incapable of managing their affairs (financially) was vigorously opposed by both the NRA and the ACLU.  That should catch your eye, because the ACLU does not recognize a Second Amendment individual right, even after the Supreme Court explicitly did.

We need creative solutions.  Lots of them.  And they have to be solutions that can get substantial buy-in from interested parties on various sides of the issue.  This is one.  I will be doing my best, if I am elected, to fashion more that I think can be enacted in the context of an American society that is starkly polarized on this issue.